Understanding the Role of ACEP Guidelines in Emergency Department Practice
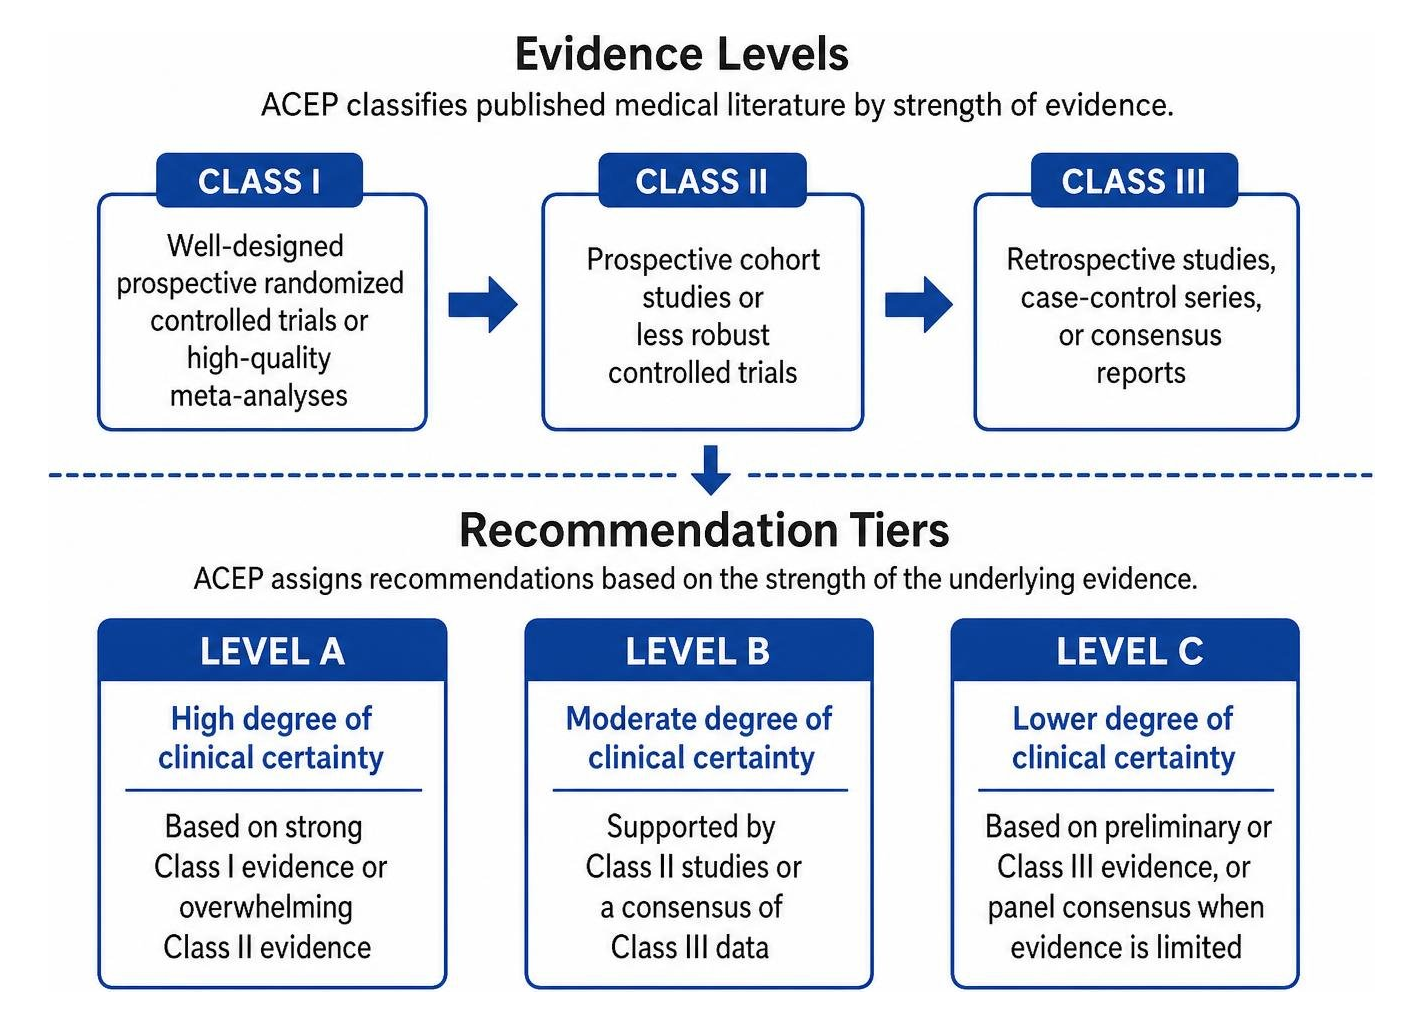
The American College of Emergency Physicians (ACEP) develops clinical policies through a rigorous, transparent methodology designed to answer focused, practical clinical questions encountered during acute patient care. These policies rely on a structured evidence grading system that classifies published medical literature from Class I (well-designed prospective randomized controlled trials or high-quality meta-analyses) to Class III (retrospective studies, case-control series, or consensus reports).
Based on the strength of this underlying medical evidence, ACEP assigns recommendations into distinct hierarchical tiers:
- Level A Recommendations: Reflect a high degree of clinical certainty based on strong Class I evidence or overwhelming Class II evidence.
- Level B Recommendations: Offer a moderate degree of clinical certainty supported by Class II studies or a consensus of Class III data.
- Level C Recommendations: Based on preliminary or Class III evidence, or in instances where panel consensus fills critical evidentiary gaps in the absence of robust literature.
In our clinical practice and expert record evaluations, these recommendations help define the objective standard of care by establishing acceptable diagnostic safety thresholds. They provide emergency physicians with validated safety margins—often targeting a missed-disease threshold below 1% to 2%—to ensure that high-risk conditions are not overlooked while preventing the physical and financial harms of over-testing. Proper application of these guidelines begins from the initial nursing assessment, where standardized triage techniques in an emergency department establish baseline vital signs and prioritize diagnostic urgency.
Evaluating Pretest Probability and Structured Prediction Rules
A central tenet across ACEP policies is the necessity of formal risk stratification before diagnostic testing is ordered. Clinicians must establish a patient’s pretest probability using structured, validated clinical prediction rules—such as the Wells score or the Revised Geneva score—rather than unstructured intuition alone.
By applying Bayesian decision models, an emergency clinician evaluates the likelihood of disease prior to testing. This process protects the patient from diagnostic cascades: an unindicated advanced diagnostic test (such as a computed tomography pulmonary angiogram) in a patient with an exceedingly low pretest probability carries a high false-positive rate, unnecessary ionizing radiation exposure, and potential contrast-induced adverse reactions. Structured prediction rules create diagnostic stewardship, aligning testing choices with scientific evidence.
Clinical Guidelines as Medicolegal Benchmarks
In litigation, medical records are evaluated through the lens of contemporaneous clinical knowledge. An adverse medical outcome alone does not establish medical negligence; instead, liability hinges on whether the provider adhered to the appropriate standard of care based on the patient’s presentation and the information available at the time.
When counsel on either side reviews an alleged case of medical malpractice in the emergency room, ACEP clinical policies serve as recognized benchmarks of accepted practice. When an emergency physician documents the structured score used, the clinical reasoning behind selecting or omitting a test, and the discharge rationale, they substantiate that thoughtful, guideline-aligned medical decision-making took place. If a clinician deviates from an established policy, the medical record should clearly articulate the patient-specific variables, comorbidities, or clinical contraindications that justified the tailored approach.
Venous Thromboembolism Management: Evidence-Based Protocols and Risk Stratification
Venous thromboembolism (VTE), encompassing deep venous thrombosis (DVT) and pulmonary embolism (PE), affects an estimated 600,000 to 900,000 American adults annually, with PE representing up to 10% of all hospital deaths. Diagnostic pathways require rapid identification of high-risk patients alongside safe exclusion strategies for low-risk individuals.
The table below outlines the primary risk stratification tools and clinical thresholds validated across emergency medicine literature:
| Tool / Metric | Target Patient Population | Primary Clinical Criteria | Guideline Threshold / Actionable Outcome |
|---|---|---|---|
| PERC Rule | Low pretest probability for PE (Wells <2 or low gestalt) | Age <50, HR <100, SpO2 ≥95%, no prior VTE, no recent surgery/trauma, no hemoptysis, no estrogen, no unilateral leg swelling | All 8 negative: PE safely excluded without D-dimer or imaging (posttest probability <2%) |
| Age-Adjusted D-Dimer | Patients >50 years with low/intermediate risk | Serum D-dimer testing (FEU) | Cutoff = Age × 10 µg/L; avoids advanced imaging in up to 30% of geriatric patients |
| PESI / sPESI | Diagnosed acute PE | Age, vitals, cancer history, heart failure, chronic lung disease, altered mentation | Class I-II (or sPESI = 0): Eligible for outpatient therapy / discharge |
| Hestia Criteria | Diagnosed acute PE | 11-item checklist (hemodynamics, bleeding risk, social support, renal/hepatic function) | All criteria negative: Safe for outpatient management on oral anticoagulation |
Applying ACEP Guidelines for Suspected Pulmonary Embolism and DVT
When evaluating a patient with suspected PE, the primary challenge is determining who requires diagnostic imaging and who can be safely discharged without further workup. For patients categorized as low pretest probability by gestalt or structured score, ACEP guidelines endorse using the Pulmonary Embolism Rule-out Criteria (PERC). The PERC rule exhibits a pooled sensitivity of 97% and a negative likelihood ratio of 0.18. In an emergency population with a baseline 10% pretest probability, a negative PERC assessment reduces the posttest probability of PE to approximately 1.9%, meeting the accepted 2% diagnostic safety threshold and eliminating the need for D-dimer testing or ionizing radiation.
For patients over the age of 50 with low-to-intermediate pretest probability who fail PERC or require lab testing, conventional D-dimer cutoffs (500 µg/L) lose specificity due to age-related physiological changes. ACEP clinical policies support the use of age-adjusted D-dimer cutoffs (calculated as patient age multiplied by 10 µg/L for those older than 50). Implementing this cutoff increases the proportion of non-high-risk patients with a negative D-dimer result by 5% to 12% without increasing missed thromboembolic events. In patients over 75 years old, age-adjusted cutoffs increase the rate of negative findings from 6% to 30% while maintaining diagnostic safety.
When diagnostic imaging reveals an isolated subsegmental pulmonary embolism (SSPE) without proximal pulmonary arterial involvement or deep vein thrombosis, ACEP clinical policy and current expert consensus highlight the safety of withholding anticoagulation in select low-risk patients. This decision requires documenting normal proximal lower-extremity duplex ultrasonography, adequate cardiopulmonary reserve, no active malignancy, and an absence of persistent risk factors, arrived at through documented shared decision-making.
Outpatient Discharge Criteria and Anticoagulation Selection for Low-Risk VTE
Historically, acute pulmonary embolism mandated immediate inpatient hospital admission. Current clinical policies, developed in alignment with multidisciplinary guidelines from the AHA, ACC, and ACCP, recognize that approximately 50% of acute PE presentations represent low-risk disease suitable for direct discharge or abbreviated observation.
Emergency clinicians identify suitable candidates using validated prognostic tools:
- Pulmonary Embolism Severity Index (PESI): Class I (score ≤65) and Class II (score 66–85) denote very low and low 30-day mortality risk.
- Simplified PESI (sPESI): A score of 0 identifies low-risk status.
- Hestia Criteria: A negative screen across 11 clinical and social safety parameters confirms readiness for outpatient treatment.
In this low-risk cohort (AHA/ACC Category A), outpatient management yields a 90-day incidence of recurrent VTE, major hemorrhage, and all-cause mortality of approximately 1.5%, 0.8%, and 1.6%, respectively—outcomes comparable to inpatient admissions.
For outpatient management of acute lower-extremity DVT and low-risk PE, direct oral anticoagulants (DOACs) are recommended over traditional low-molecular-weight heparin (LMWH) bridged to vitamin K antagonists (VKAs). High-level clinical trial data validate this approach:
- The AMPLIFY Trial: Patients with acute VTE treated with apixaban experienced a major bleeding rate of 0.6% compared to 1.8% in those receiving conventional enoxaparin/warfarin therapy (risk difference -1.1%; 95% CI -1.7 to -0.6), with equivalent efficacy in preventing recurrent VTE.
- The EINSTEIN-DVT Trial: Rivaroxaban demonstrated noninferiority for recurrent VTE prevention (2.1% vs 3.0%; HR 0.7; 95% CI 0.4 to 1.0) with an identical major bleeding rate of 8.1%.
Emergency physicians discharging low-risk VTE patients must ensure immediate access to medications, clear follow-up within 24 to 72 hours, and comprehensive patient education.
Critical Policy Updates: DOAC Reversal, Opioid Stewardship, and Asymptomatic Hypertension
Emergency departments regularly manage high-stakes decisions regarding pharmacotherapy, reversal agents, and incidental diagnostic findings. ACEP clinical policies provide clear, actionable pathways for these scenarios.
Direct Oral Anticoagulant Reversal in Life-Threatening Hemorrhage
When patients taking DOACs experience major, life-threatening hemorrhage (such as intracranial or severe gastrointestinal bleeding), emergency physicians must assess reversal options based on the specific anticoagulant:
- Dabigatran (Direct Thrombin Inhibitor): Idarucizumab is recommended as a specific reversal agent. Clinicians must weigh the clinical benefit of rapid reversal against potential post-administration thrombotic risks.
- Factor Xa Inhibitors (Apixaban, Rivaroxaban, Edoxaban): Unactivated four-factor prothrombin complex concentrate (4F-PCC) serves as the primary practical reversal strategy in many clinical settings. Andexanet alfa, an engineered decoy receptor, is an alternative; however, ACEP policy notes that decisions surrounding andexanet alfa should balance uncertain clinical outcome superiority against elevated costs and potential thrombotic complications.
- Shared Decision-Making: Given the delicate balance between stopping hemorrhage and triggering fatal thrombosis, emergency clinicians must document detailed risk-benefit discussions with the patient or their surrogate.
Prescription Drug Monitoring and Multimodal Pain Protocols
In acute pain management, ACEP guidelines emphasize multimodal analgesia to provide effective relief while minimizing reliance on opioids. The policy establishes non-opioid medications—such as oral and intravenous acetaminophen, nonsteroidal anti-inflammatory drugs (NSAIDs), sub-dissociative ketamine infusions, and regional nerve blocks—as first-line therapies.
When opioids are necessary for acute severe pain, guidelines advise prescribing the lowest effective dose of short-acting Schedule II agents for limited durations, while avoiding long-acting formulations in the emergency setting. Clinicians should routinely consult state Prescription Drug Monitoring Programs (PDMPs). Studies indicate that checking PDMPs alters prescribing decisions in up to 41% of evaluated cases, helping identify high-risk medication combinations and curb diversion without compromising acute pain relief.
Management of Asymptomatic Elevated Blood Pressure
Approximately six million emergency visits annually involve high blood pressure. ACEP clinical policies emphasize that patients presenting with asymptomatic elevated blood pressure—in the absence of symptoms or clinical signs of acute target-organ injury (such as encephalopathy, acute pulmonary edema, aortic dissection, or acute kidney injury)—do not require rapid intravenous blood pressure reduction in the emergency room.
For patients discharged home, starting an oral outpatient antihypertensive agent (such as a thiazide diuretic or ACE inhibitor) produces a modest systolic reduction of approximately 11 mmHg without increasing adverse clinical events. However, the critical standard-of-care requirement is securing confirmed, documented outpatient primary care follow-up within one to two weeks, prioritizing longitudinal management over acute interventions in the emergency department.
Bridging Clinical Policies to the Courtroom: Standard of Care and Legal Defense
In medical liability litigation involving emergency medicine, courts rely on expert testimony to evaluate whether a physician’s actions met the standard of care. This standard is defined as what a reasonably prudent emergency physician with similar training would have done under the same or similar circumstances.
When evaluating these matters, the legal analysis centers on several key elements:
- Understanding the 4 Ds of a medical malpractice lawsuit—duty, dereliction (breach of duty), direct causation, and damages.
- Establishing the 3 requirements to prove malpractice, which require demonstrating that a doctor-patient relationship existed, that the provider breached the acceptable standard of care, and that this breach directly caused compensable injury.
- Properly defining malpractice by distinguishing between an unpreventable adverse medical outcome and an actual deviation from accepted professional standards.
To withstand legal scrutiny, emergency physicians protect patient safety and mitigate medicolegal exposure by maintaining detailed medical record documentation:
- Risk Scores: Documenting the specific scores calculated (e.g., PERC, Wells, sPESI) and their clinical interpretation.
- Cognitive Differential: Outlining the diagnostic possibilities considered and the clinical reasoning for ordering or omitting specific diagnostic studies.
- Serial Re-evaluations: Recording vital sign trends, interval changes in physical examination findings, and responses to administered medications.
- Shared Decision-Making: Noting discussions with patients regarding the risks, benefits, and alternatives of outpatient therapy versus hospital admission.
- Discharge Instructions: Providing concrete, condition-specific “return-to-ED” warnings and confirming accessible, scheduled follow-up appointments.
Analyzing Deviations from ACEP Guidelines in Malpractice Claims
An adverse medical outcome alone does not establish medical negligence. In both plaintiff and defense case reviews, medical records must be examined to reconstruct what the treating clinician knew, observed, and considered at the bedside.
A deviation from an ACEP guideline does not automatically constitute a breach of duty, just as strict adherence does not guarantee immunity from liability. Clinical policies are not rigid mandates; they are flexible decision-making aids. When an emergency physician’s differential diagnosis and treatment choices deviate from a policy due to atypical presentations, multimorbidities, or patient preferences, documenting this clinical reasoning demonstrates that reasoned medical judgment occurred. As an independent medical expert, I review records to evaluate whether the documented diagnostic process, clinical monitoring, and disposition were reasonable under the circumstances.
Frequently Asked Questions About ACEP Guidelines
How does the PERC rule rule out pulmonary embolism without imaging?
The PERC rule utilizes eight clinical criteria: age under 50, pulse rate below 100 beats per minute, oxygen saturation of 95% or greater on room air, no prior history of deep venous thrombosis or pulmonary embolism, no recent trauma or surgery requiring hospitalization within the past four weeks, no hemoptysis, no exogenous estrogen use, and no unilateral leg swelling.
When applied to a patient independently determined to have a low pretest probability of pulmonary embolism (less than 15% clinical likelihood), meeting all eight criteria reduces the posttest probability of PE to under 2%. Because the risk of adverse events from diagnostic imaging (such as contrast reactions or radiation) exceeds this threshold, meeting PERC criteria rules out PE without D-dimer testing or CT pulmonary angiography.
When is it safe to discharge acute pulmonary embolism patients from the ED?
An acute pulmonary embolism patient may be considered for direct emergency department discharge on oral anticoagulation when all of the following conditions are met:
- Hemodynamic Stability: Normal systemic blood pressure, normal heart rate, and room-air oxygen saturation ≥95%.
- Low Prognostic Risk: Classification in PESI Class I or II, a simplified PESI (sPESI) score of 0, or negative Hestia criteria.
- Absence of Right Ventricular Strain: No evidence of RV dilation or dysfunction on echocardiography or CT, and normal cardiac biomarkers (troponin and BNP).
- Low Bleeding Risk: Absence of active bleeding, severe renal impairment, severe hepatic disease, or coagulopathies.
- Social Stability: A secure home environment, reliable access to prescribed anticoagulants (such as apixaban or rivaroxaban), and confirmed outpatient follow-up within 24 to 72 hours.
What role do clinical policies play in emergency medical malpractice cases?
Clinical policies published by professional organizations like ACEP provide authoritative, evidence-based definitions of acceptable clinical decision-making. In litigation, attorneys working on complex emergency department cases often ask, why do I need an expert witness?
An emergency medicine expert witness utilizes these guidelines to evaluate the medical records objectively. The expert helps counsel understand whether the treating physician’s differential diagnosis, diagnostic evaluation, and disposition aligned with accepted standards of care, or whether cognitive errors, premature closure, or lack of monitoring breached the standard and directly contributed to the patient’s injuries.
Conclusion
Understanding and applying evidence-based clinical policies lies at the heart of safe emergency medical practice and objective legal case evaluation. For emergency physicians, aligning clinical workflows with ACEP guidelines reduces cognitive error, protects against unnecessary diagnostic interventions, and ensures high-quality patient care. For attorneys handling medical malpractice matters, these guidelines serve as objective frameworks for analyzing the quality of medical decision-making in the emergency department.
Evaluating complex emergency medicine records requires an experienced perspective grounded in real-world clinical practice. For legal teams seeking objective analysis, understanding what is a medical expert witness and how an independent physician evaluates these standards is critical.
At Emergency Expert For You, Dr. Edward Mallory brings more than 30 years of clinical Emergency Medicine experience, approximately 13 years of medical expert witness experience, over 200 medical cases reviewed, and active board certification by the American Osteopathic Board of Emergency Medicine since 1993. Dr. Mallory provides thorough, unbiased medical record reviews, affidavits of merit, and expert testimony strictly within Emergency Medicine and Primary Care for both plaintiff and defense counsel across Florida and nationwide.
If you are an attorney evaluating an emergency department case, contact Dr. Mallory to discuss how an evidence-based medical record review can clarify the medical issues in your case.